When "Minimally Invasive Lifting" Becomes a Problem Requiring Repair
"I was told it was a simple lunchtime procedure — now I have dimples in my cheeks and a thread poking through my skin." At FILLER REVISION, thread lift complications are a growing category of our revision cases. Patients arrive frustrated and anxious, often after being told to "just wait for the threads to absorb" — advice that ignores the tissue damage already occurring.
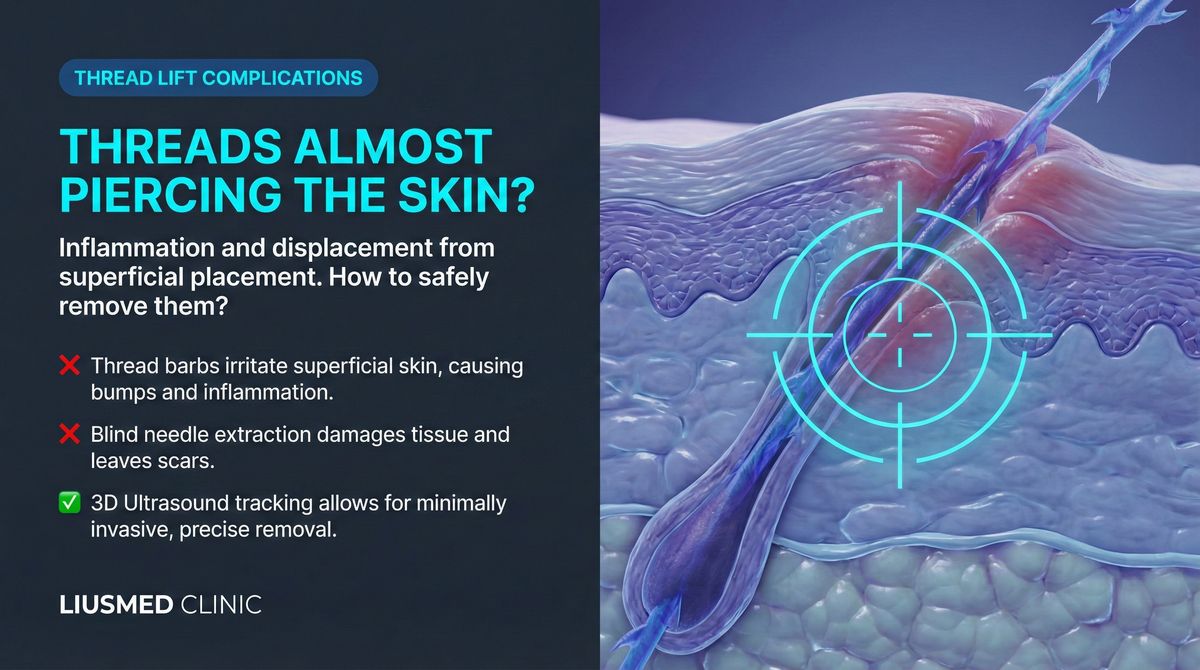
The reality is that thread lifts involve placing foreign material into subcutaneous tissue, and at FILLER REVISION we see the full spectrum of what can go wrong: thread ends protruding through the skin, visible dimpling or puckering, severe asymmetry, incorrect placement, persistent pain, and infection or granuloma formation. These problems sometimes appear immediately, sometimes emerging gradually over weeks to months.
How Common Are Thread Lift Complications?
Most problems after a thread lift are temporary swelling and bruising. The ones that stay, such as dimpling, a thread you can see or feel, or a thread poking through, are less common, but they are not rare. Pooled figures from two meta-analyses:
← Swipe to see more →
| Complication | Reported rate |
|---|---|
| Swelling | about 34–35% |
| Skin dimpling | about 7–10% |
| Visible or palpable thread | about 4–10% |
| Altered sensation (paresthesia) | about 6% |
| Thread poking through the skin | about 2% |
| Infection | about 2% |
The studies differ a lot in thread type and technique, so read these as rough ranges. Two patterns hold up: non-absorbable threads poked through more often than absorbable ones (7.6% vs 1.6%), and people over 50 had more dimpling (16% vs 5.6%) and more infection (5.9% vs 0.7%). A systematic review covering more than 14,000 patients found most side effects settle on their own; the exceptions were contour irregularities, injury to vessels or glands, infection and inflammatory reactions.
What a thread lift gone wrong looks like
In 190 patients referred to one centre after thread lifts done elsewhere, the most common problems were skin dimpling (40.5%), uneven contour (16.8%), visible threads (16.3%), infection (8.9%) and a thread poking through (5.3%). In everyday terms:
- A dent or pucker where the skin is pulled in along a thread line, often clearer when you smile or talk
- A cord or bump under the skin that you can feel, or see when light falls across the face
- A thread end coming through the skin, sometimes with a small scab or discharge
- One side swollen, red, warm or painful, which points toward infection or inflammation
For what removed threads actually look like, see Dr. Ta-Ju Liu's community post Did you know that thread lifts can actually be removed?
Common Causes of Thread Lift Failure
Technique-Related Factors
← Swipe to see more →
| Problem Type | Common Technical Cause | Consequence |
|---|---|---|
| Thread protrusion | Insufficient insertion depth, excessive tension | Infection risk, cosmetic deformity |
| Skin dimpling | Improper trajectory selection, excessive barb grip | Visible unnatural indentations |
| Asymmetry | Unequal thread count or tension between sides | May require surgical correction |
| Persistent pain | Thread contacting nerves or incorrect anchor point | Long-term discomfort |
| Rapid effect loss | Inappropriate thread selection, insufficient tissue grip | Needs retreatment |
Material-Related Factors
- PDO (Polydioxanone) threads: Absorbable but individual variation in degradation rate; sometimes incomplete degradation leaves remnants
- PCL (Polycaprolactone) threads: Slower degradation means problems persist longer
- PLLA (Poly-L-Lactic Acid) threads: Also absorbable; reliable figures for how long they take to break down are limited
- Non-absorbable threads: Permanent presence; once problems develop, physical removal is required
In studies of absorbable threads, barbed threads were linked to more complications than smooth or coned threads. Non-absorbable threads, compared with absorbable ones, had more extrusion and more altered sensation (11.7% vs 3.1%).
Patient-Related Factors
- Skin too thin to withstand thread tension
- High-mobility areas (such as perioral region) where threads easily shift
- Keloid tendency increasing granuloma risk
- Non-compliance with post-procedure instructions (premature massage, vigorous exercise)
Key Insight: At FILLER REVISION, we tell patients: thread lift failure is not necessarily "bad technique" — it is a complex outcome involving the interaction of material properties, patient conditions, and surgical skill. But regardless of cause, the question our patients face is always the same: what now? And that is where precision imaging changes everything.
Is "Waiting for It to Absorb" Really Viable?
This is the most common advice after thread lift problems: "The threads are absorbable—just wait a few months."
How long threads actually last depends on the material. PDO is usually absorbed after about six months. PCL lasts longer: in a rat study it was still in the tissue after more than a year, compared with around 24 weeks for PDO. And absorption isn't the end of the story. A study of facelifts after thread lifting found that the tissue changes threads cause last much longer than both the lift and the threads themselves.
Situations Where Waiting May Be Reasonable
- Mild early post-procedure asymmetry (may improve as swelling resolves)
- Very slight tactile abnormality (may diminish over time)
- Dimpling in the first days to weeks: in a series of 148 patients, dimpling and irregularity settled on their own within 3–7 days in all but one. Dimpling still present after about four weeks is what researchers class as a late complication, and is worth assessing
Problems That Waiting Typically Cannot Solve
- Thread protrusion: Once a thread penetrates the skin, it will not retract on its own and maintains a continuous infection pathway
- Deep dimpling: Tissue adhesions caused by threads may persist even after the thread degrades
- Infection or granuloma: Will not resolve spontaneously with thread degradation; may worsen. Infection can also appear years later: case reports describe infections three to four years after a thread lift. In another report, inflammation after PDO threads didn't settle with antibiotics, and the threads were found and removed during a biopsy
- Severe asymmetry: Requires active intervention to correct
← Swipe to see more →
| Problem | Viability of Waiting | Risk of Waiting |
|---|---|---|
| Thread protrusion | Not viable | Stays an open route for infection |
| Skin dimpling | Limited | May form permanent scarring |
| Asymmetry | Mild cases only | Severe cases need timely intervention |
| Persistent pain | Can observe for weeks | Nerve damage harder to reverse with delay |
| Infection | Not viable | May spread or form abscess |
| Granuloma | Limited | May continue enlarging |
Key Insight: "Absorbable" does not mean "the problem will disappear on its own." The thread degrades, but the tissue reactions it caused—adhesions, fibrosis, granulomas—may persist long after the thread is gone. Waiting for the thread to absorb addresses the "cause" but not the "effect," which has taken on an independent existence.
The FILLER REVISION Approach: Precision Thread Removal Under Ultrasound (Ultrasonography)
At FILLER REVISION, we approach thread lift complications with the same imaging-first philosophy we use for filler problems. High-resolution ultrasound helps locate the position, depth and path of problem threads, including threads that have shifted or fragmented, and shows any infection or inflammation around them. This is critical because barbed threads cannot simply be pulled out; forceful blind removal risks tearing tissue and causing more damage. Under real-time ultrasound guidance, we can trace each problem thread along its path, release adhesions, and remove it with minimal tissue disruption. For patients with dimpling caused by tissue adhesions rather than the thread itself, our imaging confirms this distinction so we can address the adhesion directly instead of searching for a thread that may have already degraded.
Removal is done through a pinhole of about 2mm under ultrasound guidance, with no incision and no stitches. When there are many threads or they cover a wide area, removal may be split into zones or sessions, still through pinholes.
Challenges in Managing Thread Lift Failures
Why Managing Thread Problems Is More Difficult Than Expected
- Thread localization is challenging: Implanted threads are invisible to the eye and not always accurately located by touch, especially threads that are partially degraded or displaced
- Barbed design increases removal difficulty: Barbed threads cannot simply be "pulled out"—forceful extraction may cause greater tissue damage
- Multiple intertwined threads: A single procedure may place 10-20 threads, requiring individual attention during removal
- Surrounding tissue adhesion: Threads have formed adhesions with surrounding tissue, requiring simultaneous adhesion release during extraction
The Role of Ultrasound in Thread Problem Management
Similar to filler management, ultrasound plays a critical diagnostic and treatment-guidance role in thread problems:
- Precise localization: Confirms the position, depth and path of problem threads
- Status assessment: Determines whether threads are intact, partially degraded, or fragmented
- Tissue reaction evaluation: Observes whether inflammation, granuloma, or infection exists around threads
- Guided removal: Ultrasound-guided precision removal of problem threads, minimizing unnecessary tissue damage
- Post-procedure confirmation: Checks what has been removed and whether any problem thread remains
For more on ultrasound-guided extraction techniques: Precision Extraction Technique. For the complete evaluation process: Filler Repair Evaluation Process.
When Is the Best Time to Remove a Problem Thread?
A thread that is poking through or infected doesn't need to wait. In a series of 30 patients with complications after nose thread lifts, the authors concluded that infection "always warrants thread removal". Dimpling or unevenness is different: researchers class dimpling that lasts beyond four weeks as a late complication, so give the swelling time to settle and reassess if it is still there after that. Animal studies also show a fibrous capsule forming around threads in the weeks after placement; that bond with the surrounding tissue is one reason a thread that has been in for a long time takes more care to remove. When to remove yours is decided after an ultrasound assessment.
Management Strategies for Different Problems
Thread Protrusion
First: don't pull or cut it yourself. The barbs grip the tissue, so pulling can tear it, and cutting it short leaves the rest of the thread under the skin. Keep the area clean and get it seen soon.
Urgency: High—ongoing infection risk
Approach:
- Localize the complete path of the protruding thread
- Remove the entire thread from the entry point
- Clean the infection tract
- Short-course antibiotics if necessary
Bumps Rising One by One Under the Skin (Knotted, Tangled Thread)
First: don't squeeze or pick at them. A bump may be knotted thread underneath, and handling it yourself invites infection; have ultrasound show where the thread is and what shape it has first.
Urgency: Moderate—not urgent, but "absorbable" does not mean it will go away soon
Approach:
- Use ultrasound to confirm the position and shape of the thread at each bump
- Remove the whole thread when it can come out intact
- For a thread anchored tightly underneath, remove only the segment causing the bump
We treated a patient with bumps rising one by one at her temple and behind her ear: four months on, her absorbable threads were still strong. Of 6 threads, 1 came out whole and 5 had only the bulging segment removed; at follow-up they were much better, with a slight bump remaining. The full case and video are on this case record.
Skin Dimpling
Timing: Dimpling in the first few weeks often eases as swelling settles; if it is still there after about four weeks, have it assessed.
Urgency: Moderate—may form permanent changes
Approach:
- Ultrasound to confirm cause of dimpling (thread tension vs. tissue adhesion)
- If thread is still present, remove or adjust the segment causing dimpling
- If caused by adhesion, adhesion release may be necessary
- Severe cases may require subsequent restorative filling
Severe Asymmetry
Urgency: Moderate—affects appearance and psychology
Approach:
- Ultrasound assessment of actual thread position and tension on both sides
- Based on findings, determine approach: remove excess threads on one side, adjust tension, or redo both sides
- Must consider whether asymmetry is from threads or pre-existing
Nose Thread Lift Gone Wrong
Threads used to lift the nose tip or bridge bring their own problems. In 30 patients seen for complications after nose thread lifts, the most common were infection (46.7%) and a thread coming through the skin (30%), followed by chronic inflammation (16.7%) and dimpling (6.7%). Problems can also appear very late: barbed threads in the nose have caused a lump as late as 10 years afterwards. Ultrasound helps find remaining threads and map the infected area. For lumps on the nose from filler rather than threads, see delayed nose filler lumps and granulomas.
Key Insight: Managing thread problems requires precision—precisely locating the problem, precisely assessing severity, and precisely executing the repair. Blindly "doing it again" or "waiting for absorption" are not effective solutions. The prerequisite for precision is clear visualization, which is exactly where ultrasound provides its value.
Prevention and When to Seek Help
Considerations to Reduce Thread Lift Risk
- Choose a physician with extensive thread lift experience
- Understand whether your skin condition is suitable for thread lifting
- Ask about thread material, quantity, and expected outcomes before the procedure
- Confirm post-procedure care instructions
When You Should Seek Medical Attention
- Thread ends protruding through skin—seek help immediately
- Pain or discomfort persisting more than two weeks
- Visible dimpling or asymmetry showing no improvement trend
- Signs of infection post-procedure: redness, swelling, warmth
- Swelling or pain in front of the ear or along the jaw: threads can injure the parotid (salivary) gland
- Weakness on one side of the face
Schedule a consultation for professional evaluation and the repair approach best suited to your situation.
Conclusion
If you are dealing with thread protrusion, dimpling, asymmetry, or pain after a thread lift, FILLER REVISION specializes in ultrasound-guided thread removal and repair. We locate problem threads with ultrasound and remove them through a pinhole with minimal tissue disruption — no more waiting for absorption that may never resolve the underlying damage.
If a thread end poking through the skin or recurring inflammation is your main concern, the dedicated guide on thread protrusion and inflammation after a thread lift walks through that specific scenario.
If "just wait" has not worked and your thread lift complications persist, book a consultation →
Frequently Asked Questions
My old clinic told me to just wait for the threads to absorb. Will my thread lift problem really go away on its own?
Waiting may be reasonable only for mild early asymmetry that can improve as swelling resolves, or very slight tactile abnormality. But "absorbable" does not mean the problem will disappear: the thread degrades, yet the tissue reactions it caused — adhesions, fibrosis, granulomas — may persist long after the thread is gone. Thread protrusion, infection, and severe asymmetry typically will not resolve by waiting and may worsen, so these need active intervention rather than more waiting.
Can a protruding or barbed (cog) thread just be pulled out?
No. Barbed (cog) threads cannot simply be pulled out — forceful blind removal risks tearing tissue and causing more damage. The threads are invisible to the eye and not always accurately located by touch, especially when partially degraded or displaced, and they often form adhesions with surrounding tissue. This is why FILLER REVISION uses real-time ultrasound to trace each problem thread along its path, release adhesions, and remove it with minimal tissue disruption.
I have a dimple in my cheek after my thread lift. Is it from the thread itself or from something else?
Dimpling can be caused either by the thread itself (such as thread tension) or by tissue adhesions, and these need different repair strategies. Ultrasound distinguishes which is the cause: if the thread is still present, the segment causing the dimpling can be removed or adjusted; if it is from adhesion, adhesion release may be necessary. Severe cases may need subsequent restorative filling. This is why confirming the cause by imaging first matters, rather than searching for a thread that may have already degraded.
When should I seek medical attention after a thread lift?
Seek help immediately if a thread end is protruding through the skin, because this maintains a continuous infection pathway. You should also seek attention for pain or discomfort persisting more than two weeks, visible dimpling or asymmetry showing no improvement trend, or signs of infection such as redness, swelling, and warmth. Early intervention matters because waiting increases infection risk, scarring, and nerve damage that becomes harder to reverse.
Does a thread lift failure mean my original doctor had bad technique?
Not necessarily. Thread lift failure is a complex outcome involving the interaction of material properties, patient conditions, and surgical skill — for example, threads behave differently by material, and patient factors like skin too thin to withstand tension or high-mobility areas where threads shift can contribute. But regardless of cause, the question patients face is always the same: what now? That is where precision imaging is used to identify the actual problem and plan the right repair.
A thread is poking out of my skin. Can I pull it or cut it off myself?
No. Barbed threads grip the tissue, so pulling can tear it, and cutting it short leaves the rest under the skin, where the exposed end has already opened a route for infection. Keep the area clean, don't push it back in, and have it assessed soon so the whole thread can be traced and removed under ultrasound.
How long do thread lift threads take to dissolve?
It depends on the material. PDO threads are usually absorbed after about six months. PCL lasts longer and, in a rat study, was still present after more than a year. Dissolving doesn't always end the problem: the fibrosis and adhesions a thread causes can last well beyond the thread itself.
References
- Niu Z, Zhang K, Yao W, Li Y, Jiang W, Zhang Q, et al. A Meta-Analysis and Systematic Review of the Incidences of Complications Following Facial Thread-Lifting. Aesthetic Plast Surg. 2021;45(5):2148-2158. PMID: 33821308. DOI: 10.1007/s00266-021-02256-w
- Zhou X, Zhuang S. A meta-analysis of complications of thread lifting. Front Surg. 2026;13:1769458. PMID: 41988336. DOI: 10.3389/fsurg.2026.1769458
- Pham CT, Chu S, Foulad DP, Mesinkovska NA. Safety Profile of Thread Lifts on the Face and Neck: An Evidence-Based Systematic Review. Dermatol Surg. 2021;47(11):1460-1465. PMID: 34699439. DOI: 10.1097/DSS.0000000000003189
- Li YL, Li ZH, Chen XY, Xing WS, Hu JT. Facial Thread Lifting Complications in China: Analysis and Treatment. Plast Reconstr Surg Glob Open. 2021;9(9):e3820. PMID: 34549008. DOI: 10.1097/GOX.0000000000003820
- Ojha AS, Farahbakhsh N, Saikaly SK. An Assessment and Comparison of Adverse Effect Rates in Differing Absorbable Thread Lift Suture Materials. Dermatol Surg. 2025;51(3):272-276. PMID: 39442180. DOI: 10.1097/DSS.0000000000004466
- Sarigul Guduk S, Karaca N. Safety and complications of absorbable threads made of poly-L-lactic acid and poly lactide/glycolide: Experience with 148 consecutive patients. J Cosmet Dermatol. 2018;17(6):1189-1193. PMID: 29607627. DOI: 10.1111/jocd.12519
- Kim HJ, Lee SJ, Lee JH, Kim SH, Suh IS, Jeong HS. Clinical Features of Skin Infection After Rhinoplasty with Only Absorbable Thread (Polydioxanone) in Oriental Traditional Medicine: A Case Series Study. Aesthetic Plast Surg. 2020;44(1):139-147. PMID: 31797043. DOI: 10.1007/s00266-019-01550-y
- Ha YI, Kim JH, Park ES. Histological and molecular biological analysis on the reaction of absorbable thread; Polydioxanone and polycaprolactone in rat model. J Cosmet Dermatol. 2022;21(7):2774-2782. PMID: 34847267. DOI: 10.1111/jocd.14587
- Yordanov YP. The Facelift After Thread Lifting: Surgical and Aesthetic Complications. Aesthetic Plast Surg. 2025;49(22):6234-6239. PMID: 40775188. DOI: 10.1007/s00266-025-05091-5
- Chen Y, Hu J, Xing J, Li Y, Xu Y, Li N, et al. Complications following thread rhinoplasty. J Cosmet Dermatol. 2022;21(10):4722-4726. PMID: 35506191. DOI: 10.1111/jocd.15041
- Kim KS, Min HJ. Benign Nasal Mass as a Delayed Complication of Barbed Thread Rhinoplasty. J Craniofac Surg. 2022;33(5):e503-e505. PMID: 34897200. DOI: 10.1097/SCS.0000000000008434
- Kim J, Zheng Z, Kim H, Nam KA, Chung KY. Investigation on the Cutaneous Change Induced by Face-Lifting Monodirectional Barbed Polydioxanone Thread. Dermatol Surg. 2017;43(1):74-80. PMID: 27748691. DOI: 10.1097/DSS.0000000000000925
- Wang Y, Yang L, Li M, Long J. Rare case of late-onset chronic purulent skin and soft tissue infection after nonabsorbable thread lifting and treatment. J Cosmet Dermatol. 2021;20(10):3291-3293. PMID: 33615638. DOI: 10.1111/jocd.14015
- Ahn SK, Choi HJ. Complication After PDO Threads Lift. J Craniofac Surg. 2019;30(5):e467-e469. PMID: 31299818. DOI: 10.1097/SCS.0000000000005644
- Xu F, Chu H. Suture remnant-induced sialolithiasis and suppurative parotitis: A delayed complication following facial thread lifting. J Stomatol Oral Maxillofac Surg. 2026;127(5):102823. PMID: 42105917. DOI: 10.1016/j.jormas.2026.102823
- Kim JS, Yang EJ, Kim WR, Lee W, Kim HJ, Yi KH. Ultrasound-guided thread lifting for the prevention of parotid gland and diagnosing parotid duct complications. Skin Res Technol. 2023;29(12):e13535. PMID: 38093502. DOI: 10.1111/srt.13535